The heart and kidneys work together to maintain circulation, fluid balance and overall health—when one organ becomes impaired, the other is often affected. Understanding the heart and kidney connection can help address care gaps for the millions of people with both heart failure and impaired kidney function, a combination associated with higher mortality and hospitalisation rates, significant treatment challenges and poorer overall cardiovascular and kidney health compared to those with either disease alone.
A deeper connection: heart failure and impaired kidney function
Heart failure (HF) and reduced kidney function are among the most common chronic health conditions worldwide. They frequently coexist and are closely interconnected through shared biological pathways: approximately one in two people living with HF have impaired kidney function.1-3
Although often considered separate diseases, dysfunction in the heart and kidneys can reinforce each other, with decline in one accelerating decline in the other.1,3 Understanding this cardiorenal relationship is essential for early recognition and diagnosis, and to better define treatment innovations that are needed for this large and growing patient population.
How heart failure and impaired kidney function affect patient outcomes
People living with HF and impaired kidney function experience substantially worse clinical outcomes than those with either condition alone.4-6 Studies have shown that declining kidney function is associated with higher rates of HF hospitalisation, faster disease progression and increased mortality in HF patients.5,6 Likewise, among people with chronic kidney disease (CKD), HF is associated with accelerated kidney disease progression and a greater risk of death.5 Together, these findings highlight the significant burden of the cardiorenal syndrome and the need for more effective treatment.

Patients with HF and severe kidney dysfunction have over ~4x higher in-hospital mortality risk compared to those with normal kidney function6*
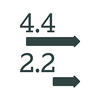
50% reduction in median survival in patients with HF and impaired kidney function** compared to patients with HF alone (from 4.4 to 2.2 years)4

Patients with HF and impaired kidney function account for 9 million HF hospitalisations annually4,5,7-9***
Greater HF hospitalisation burden, reflected by ≥2 HF hospitalisations, was associated with approximately 2-fold higher risk of CKD progression and 2- to 3-fold higher risk of all-cause mortality5
* Normal kidney function: eGFR = ≥90 mL/min/1.73m2; Severe kidney dysfunction: eGFR = <30 mL/min/1.73m2.
** Impaired kidney function: eGFR = 20-60 mL/min/1.73m2.
***Assumes 15M global hHF patients, with 60% attributable to impaired kidney function based on 1.5× higher risk versus HF alone.
Despite advances in foundational medical therapy (FMT) for HF treatment across the full range of ejection fraction, these therapies are often underutilised in patients with HF and impaired kidney function.6,10,11 Mineralocorticoid receptor antagonists (MRAs), for example, are a key component of FMT, but up to 70% of patients with HF and impaired kidney function are not receiving MRA treatment, with hyperkalaemia risk posing a significant challenge.6,10-12 This highlights how patients with HF and impaired kidney function and their treating physicians face complexity in treatment management that may result in further exposure to risk.
For people living with both heart failure and impaired kidney function, the burden extends far beyond managing two diagnoses. They often face more hospital visits, greater uncertainty and more complex treatment decisions while simply trying to maintain their daily lives. As our understanding of the cardiorenal connection grows, there is an opportunity to eliminate the barriers that stand between patients and better long-term outcomes.

How the connected biological pathways between the heart and kidney impact cardiorenal disease
The heart and kidneys perform distinct functions, but they operate as part of an interconnected physiological system responsible for general cardiorenal health that is essential for good health-related quality of life.1,13,14 The heart delivers oxygenated blood throughout the body, while the kidneys remove waste from the body and regulate fluid balance, electrolyte levels and blood pressure.13-15
When heart function declines, reduced cardiac output and increased venous congestion can impair kidney blood flow and function.1,14,15 Conversely, worsening kidney function can contribute to fluid overload, neurohormonal activation, vascular dysfunction and increased cardiac stress.1,14,15 This bidirectional heart and kidney connection means that decline in one organ can accelerate decline in the other.3 As a result, patients with both conditions frequently experience worse cardiovascular and renal outcomes than patients with only heart or kidney disease.5,6
HF and impaired kidney function are linked not only by physiology, but also by shared cardiorenal disease mechanisms:
- Hemodynamic stress: Persistent changes in blood flow, blood pressure and fluid volume place stress on the cardiovascular and renal systems, accelerating disease progression and organ damage.1,3,16
- Neurohormonal activation: Chronic activation of the renin–angiotensin–aldosterone system (RAAS) pathway and sympathetic nervous system is a hallmark of both HF and kidney disease, promoting sodium retention, vasoconstriction and tissue injury.1,3,16,17
- Inflammation and fibrosis: Chronic inflammatory signalling can contribute to structural remodelling in both the heart and kidneys, reducing organ function over time.1,3,16
- Metabolic dysfunction: Metabolic disturbances can affect vascular health, inflammation and cellular energy pathways, further amplifying cardiorenal risk.1,3,16,18

As a cardiologist, I’ve seen first-hand the challenges faced every day in optimising the management of heart failure with impaired kidney function. The choices are difficult for both patient and physician, and often the choice is between potentially increasing hyperkalaemia risk or compromising evidence-based care. As our scientific understanding of the shared biological pathways in cardiorenal disease evolves, taking a more integrated view of cardiovascular and kidney health has the potential to improve how we recognise risk, implement optimal care and ultimately improve outcomes for patients.

Exploring opportunities for complementary mechanisms to drive simultaneous cardiorenal disease change
Among these interconnected pathways, mineralocorticoid receptor (MR) signalling has emerged as an important biological driver in cardiorenal disease.19 Excessive activation of the MR pathway can lead to HF and impaired kidney function and may contribute to inflammation and fibrosis-induced tissue damage in the heart and kidneys.19 Targeting MR signalling has become an important therapeutic strategy in HF, including the integration of therapies like MRAs into FMT.10,15 However, use of current MRAs is limited by increased hyperkalaemia risk, especially in HF patients with impaired kidney function.6,10,11
Emerging research is investigating new approaches that seek to preserve the benefits associated with targeting MR biology while addressing treatment challenges associated with electrolyte management. Research is also exploring how using complementary mechanisms of FMT may help address the interconnected drivers of cardiorenal disease more effectively than single-pathway approaches alone.19,20
AstraZeneca is committed to advancing the science for cardiorenal disease
The growing understanding of cardiorenal disease has changed how researchers and clinicians think about HF and impaired kidney function—rather than viewing these conditions as separate conditions, evidence increasingly supports a whole-patient perspective that recognizes the shared pathways linking cardiovascular, kidney and metabolic health.13,14
AstraZeneca is committed to advancing research across these disease areas, with the goal of furthering cardiorenal research, improving understanding of interconnected disease biology and innovating beyond current cardiorenal therapies to ultimately remove barriers to optimal care for physicians and patients with HF and impaired kidney function.
You may also like


References
- Ryan DK, et al. Management of Heart Failure in Patients with Chronic Kidney Disease. Eur Cardiol. 2022;17:e17.
- McAlister FA, et al. Renal dysfunction in patients with heart failure with preserved versus reduced ejection fraction: impact of the new Chronic Kidney Disease-Epidemiology Collaboration Group formula. Circ Heart Fail. 2012;5(3):309-14.
- Lala A, et al. The interplay between heart failure and chronic kidney disease. Diabetes Obes Metab. 2025;27(7):3568-3582.
- Lawson CA, et al. Outcome trends in people with heart failure, type 2 diabetes mellitus and chronic kidney disease in the UK over twenty years. EClinicalMedicine. 2021;32:100739.
- Bansal N, et al. Burden and Outcomes of Heart Failure Hospitalizations in Adults With Chronic Kidney Disease. J Am Coll Cardiol. 2019;73(21):2691-2700.
- Patel RB, et al. Kidney Function and Outcomes in Patients Hospitalized With Heart Failure. J Am Coll Cardiol. 2021;78(4):330-343.
- Palaniappan LP, et al. 2026 Heart Disease and Stroke Statistics: A Report of US and Global Data From the American Heart Association. Circulation. 2026;153(9):e275-e906.
- Rangaswami J, et al. Cardiorenal syndrome: Classification, pathophysiology, diagnosis, and treatment strategies: A scientific statement from the American Heart Association. Circulation. 2019;139(16):e840-e878.
- Savarese G, et al. Global Public Health Burden of Heart Failure. Card Fail Rev. 2017;3(1):7-11.
- Heidenreich PA, et al. 2022 AHA/ACC/HFSA Guideline for the management of heart failure: a report of the American College of Cardiology/American Heart Association joint committee on clinical practice guidelines. Circulation. 2022;145(18):e895-e1032.
- Rossignol P, et al. Unravelling the interplay between hyperkalaemia, renin-angiotensin-aldosterone inhibitor use and clinical outcomes. Data from 9222 chronic heart failure patients of the ESC-HFA-EORP Heart Failure Long-Term Registry. Eur J Heart Fail. 2020;22(8):1378-1389.
- Dev S, et al. Temporal Trends and Hospital Variation in Mineralocorticoid Receptor Antagonist Use in Veterans Discharged With Heart Failure. Journal of the American Heart Association. 2015;4(12):e002268.
- National Kidney Foundation. (2024). The Heart and Kidney Connection. https://www.kidney.org/kidney-topics/heart-and-kidney-connection. (Accessed August 2026)
- Cleveland Clinic. Cardiorenal Syndrome. https://my.clevelandclinic.org/health/diseases/25240-cardiorenal-syndrome. (Accessed August 2026)
- Køber L, et al. 2026 ESC Guidelines for the management of heart failure: Developed by the task force for the management of heart failure of the European Society of Cardiology (ESC)With the special contribution of the Heart Failure Association (HFA) of the ESCEndorsed by the European Association for Cardio-Thoracic Surgery (EACTS). European Heart Journal. 2026.
- Segall L, et al. Heart failure in patients with chronic kidney disease: a systematic integrative review. Biomed Res Int. 2014;2014:937398.
- Kaur J, et al., Physiology, Renin Angiotensin System. [Updated 2026 Feb 21], In StatPearls [Internet]. 2026 Jan-, StatPearls Publishing: Treasure Island (FL).
- Tanasescu MD, et al. Metabolic Dysfunction at the Core: Revisiting the Overlap of Cardiovascular, Renal, Hepatic, and Endocrine Disorders. Life (Basel). 2026;16(1).
- 1Georgianos PI, et al. Mineralocorticoid Receptor Antagonism in Chronic Kidney Disease. Kidney Int Rep. 2021;6(9):2281-2291.
- Chaudhuri A, et al. Improving the residual risk of renal and cardiovascular outcomes in diabetic kidney disease: A review of pathophysiology, mechanisms, and evidence from recent trials. Diabetes Obes Metab. 2022;24(3):365-376.
Veeva ID: Z4-85138
Date of preparation: September 2026